Visual Differences: How to Instantly Tell Decorticate from Decerebrate Posturing
 By Sarah Jenkins
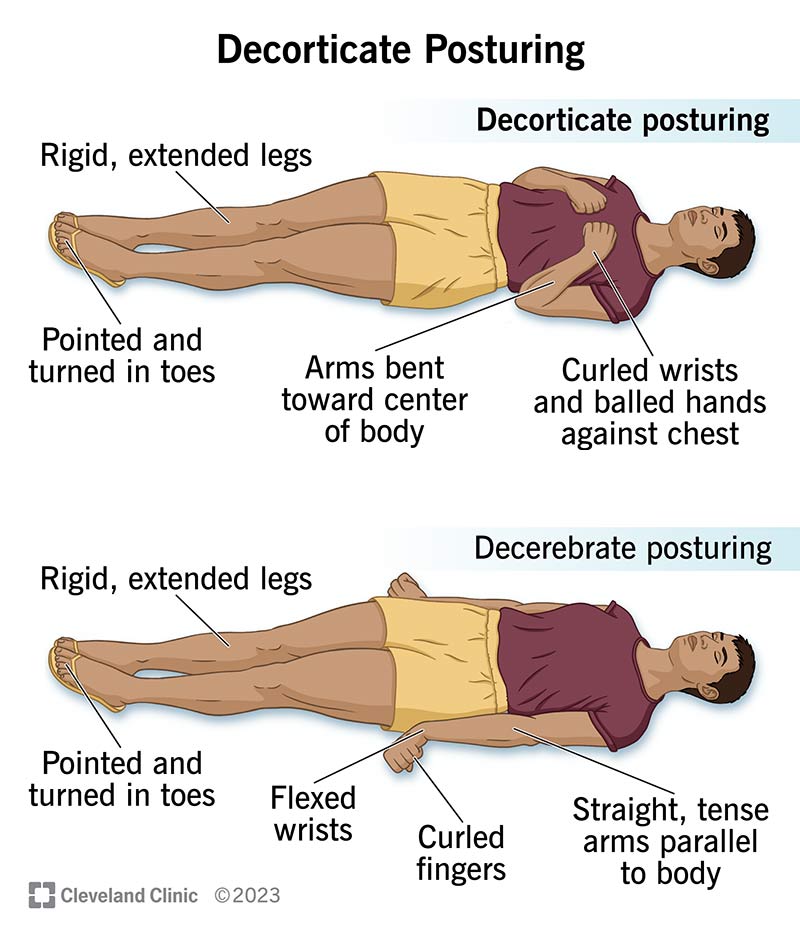
Q1: Can a patient present with decorticate posturing on one side and decerebrate on the other?
Yes. This presentation is known as uncal or asymmetric posturing. It occurs when focal lesions, such as an expanding unilateral epidural or subdural hematoma, compress the midbrain on one side first. The patient may show decorticate flexion on the side contralateral to the cortical lesion, then shift to decerebrate extension on the ipsilateral side as the uncus herniates across the tentorial notch.
Q2: Is decerebrate posturing always fatal?
No, but it carries a poor prognosis that demands immediate intervention. Decerebrate posturing indicates severe dysfunction within the midbrain and upper pons. However, prompt interventions, such as surgical evacuation of intracranial hematomas, hyperosmolar therapy with hypertonic saline or mannitol, or rapid correction of severe metabolic shifts, can restore brain perfusion and reverse the posture before permanent brainstem infarction occurs.
Q3: How does medical paralysis affect the assessment of abnormal posturing?
Paralytic agents completely wipe out abnormal posturing. Neuromuscular blocking agents like rocuronium or vecuronium block acetylcholine receptors at the neuromuscular junction, leaving the patient flaccid regardless of brainstem activity. In these situations, the motor component of the Glasgow Coma Scale cannot be tested. Critical care teams instead rely on automated pupillometry, continuous electroencephalography (EEG), and invasive intracranial pressure monitoring.
Sarah Jenkins is a veteran tech journalist with over 12 years of experience covering artificial intelligence, mobile innovations, and digital ethics. Her insights have appeared in leading technology publications worldwide.
