Unpacking the 11X Anesthesia Warning: Clinical Evidence on Ozempic Complications
 By Maya Lin-Takahashi
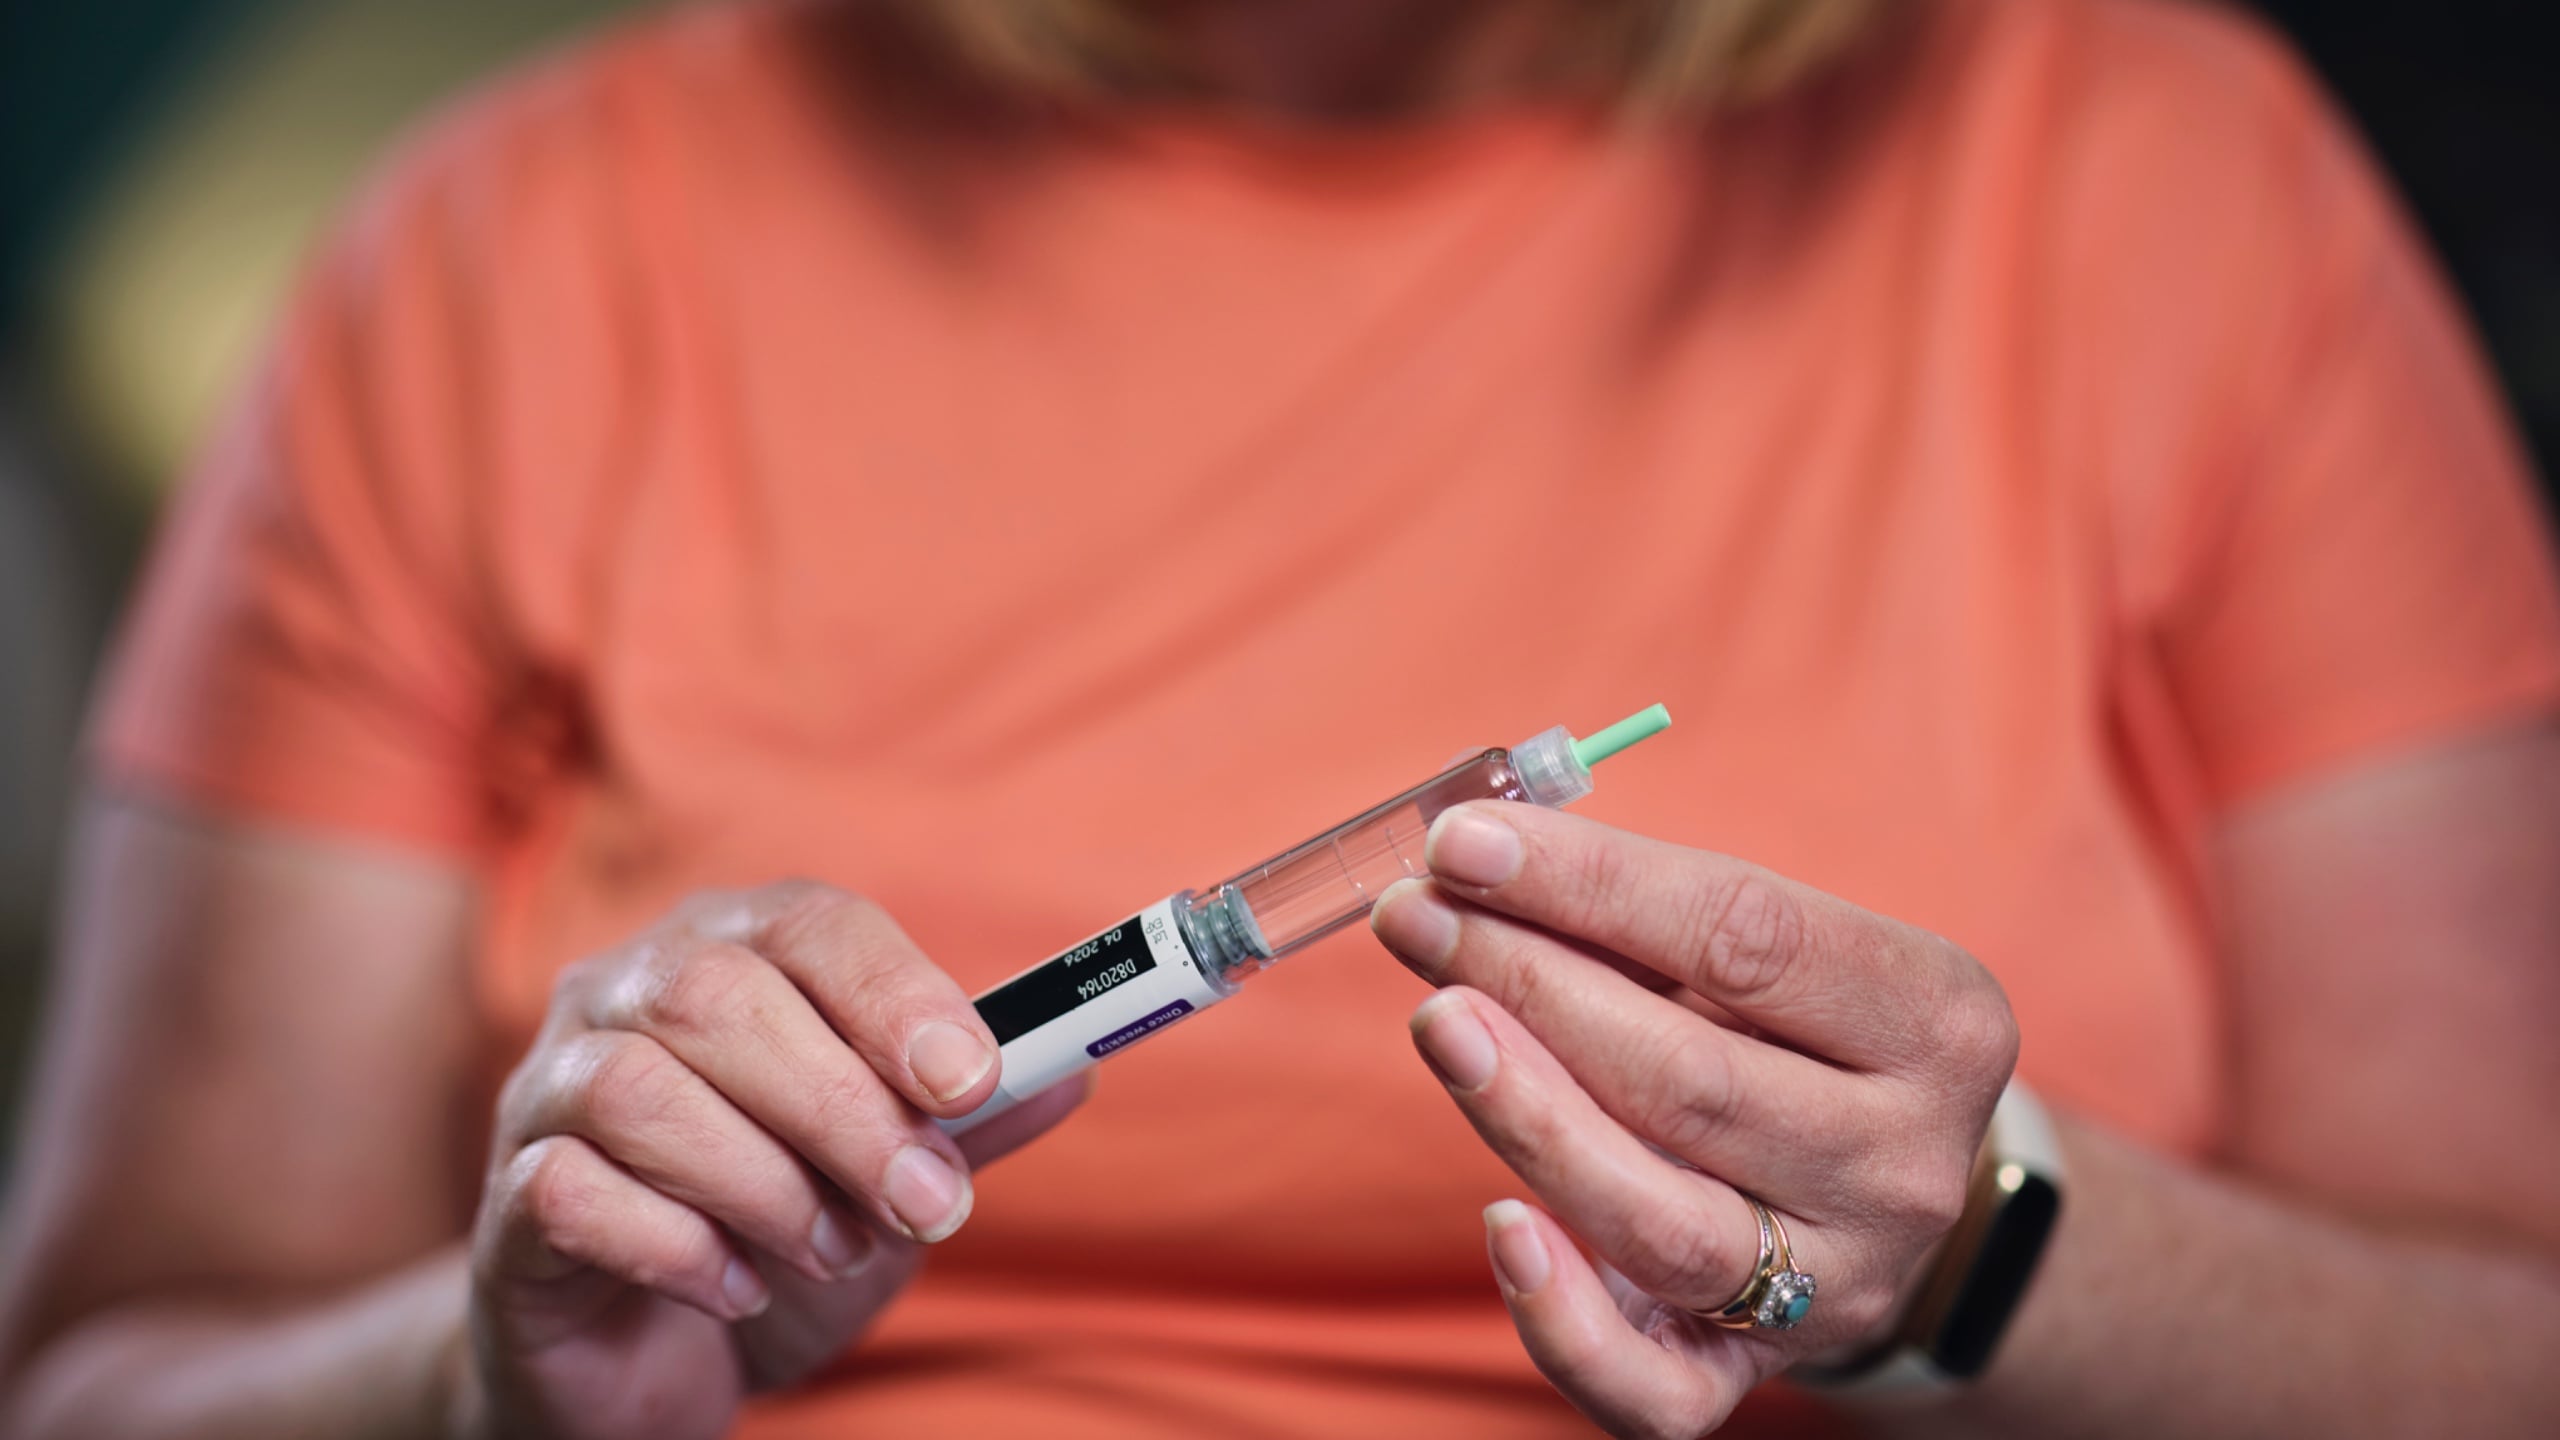
The human stomach typically clears liquids within two hours and light meals within six. GLP-1 receptor agonists disrupt this mechanical predictability. The drugs mimic human glucagon-like peptide-1, stimulating insulin production while slowing gastric motility to prolong satiety.
Under ordinary circumstances, slowed digestion helps patients consume fewer calories. Inside an operating theater, it creates a silent hazard. Anesthesiologists rely entirely on an empty stomach to prevent regurgitation when inserting an endotracheal tube or inducing twilight sedation. When neuromuscular blocking agents paralyze the patient, the lower esophageal sphincter relaxes.
If the stomach remains full, intra-abdominal pressure forces caustic gastric fluid up through the esophagus and directly into the bronchial tree. The resulting chemical pneumonitis destroys delicate lung tissue, demands immediate mechanical ventilation, and carries significant mortality rates.
Medical teams report cases of patients who followed strict liquid diets for 24 hours prior to surgery, yet regurgitated whole, identifiable food items upon induction. The drug overrides normal circadian digestive transit, rendering standard preparation protocols obsolete.
Maya is a hardware enthusiast who tests and reviews smart home devices, smartphones, wearables, and audio gear. She focuses on practical consumer value and build quality.
