Assessing Injury Severity: Fact-Checking Pitch Disasters and Geopolitical Wound Claims
 By James H. Sterling
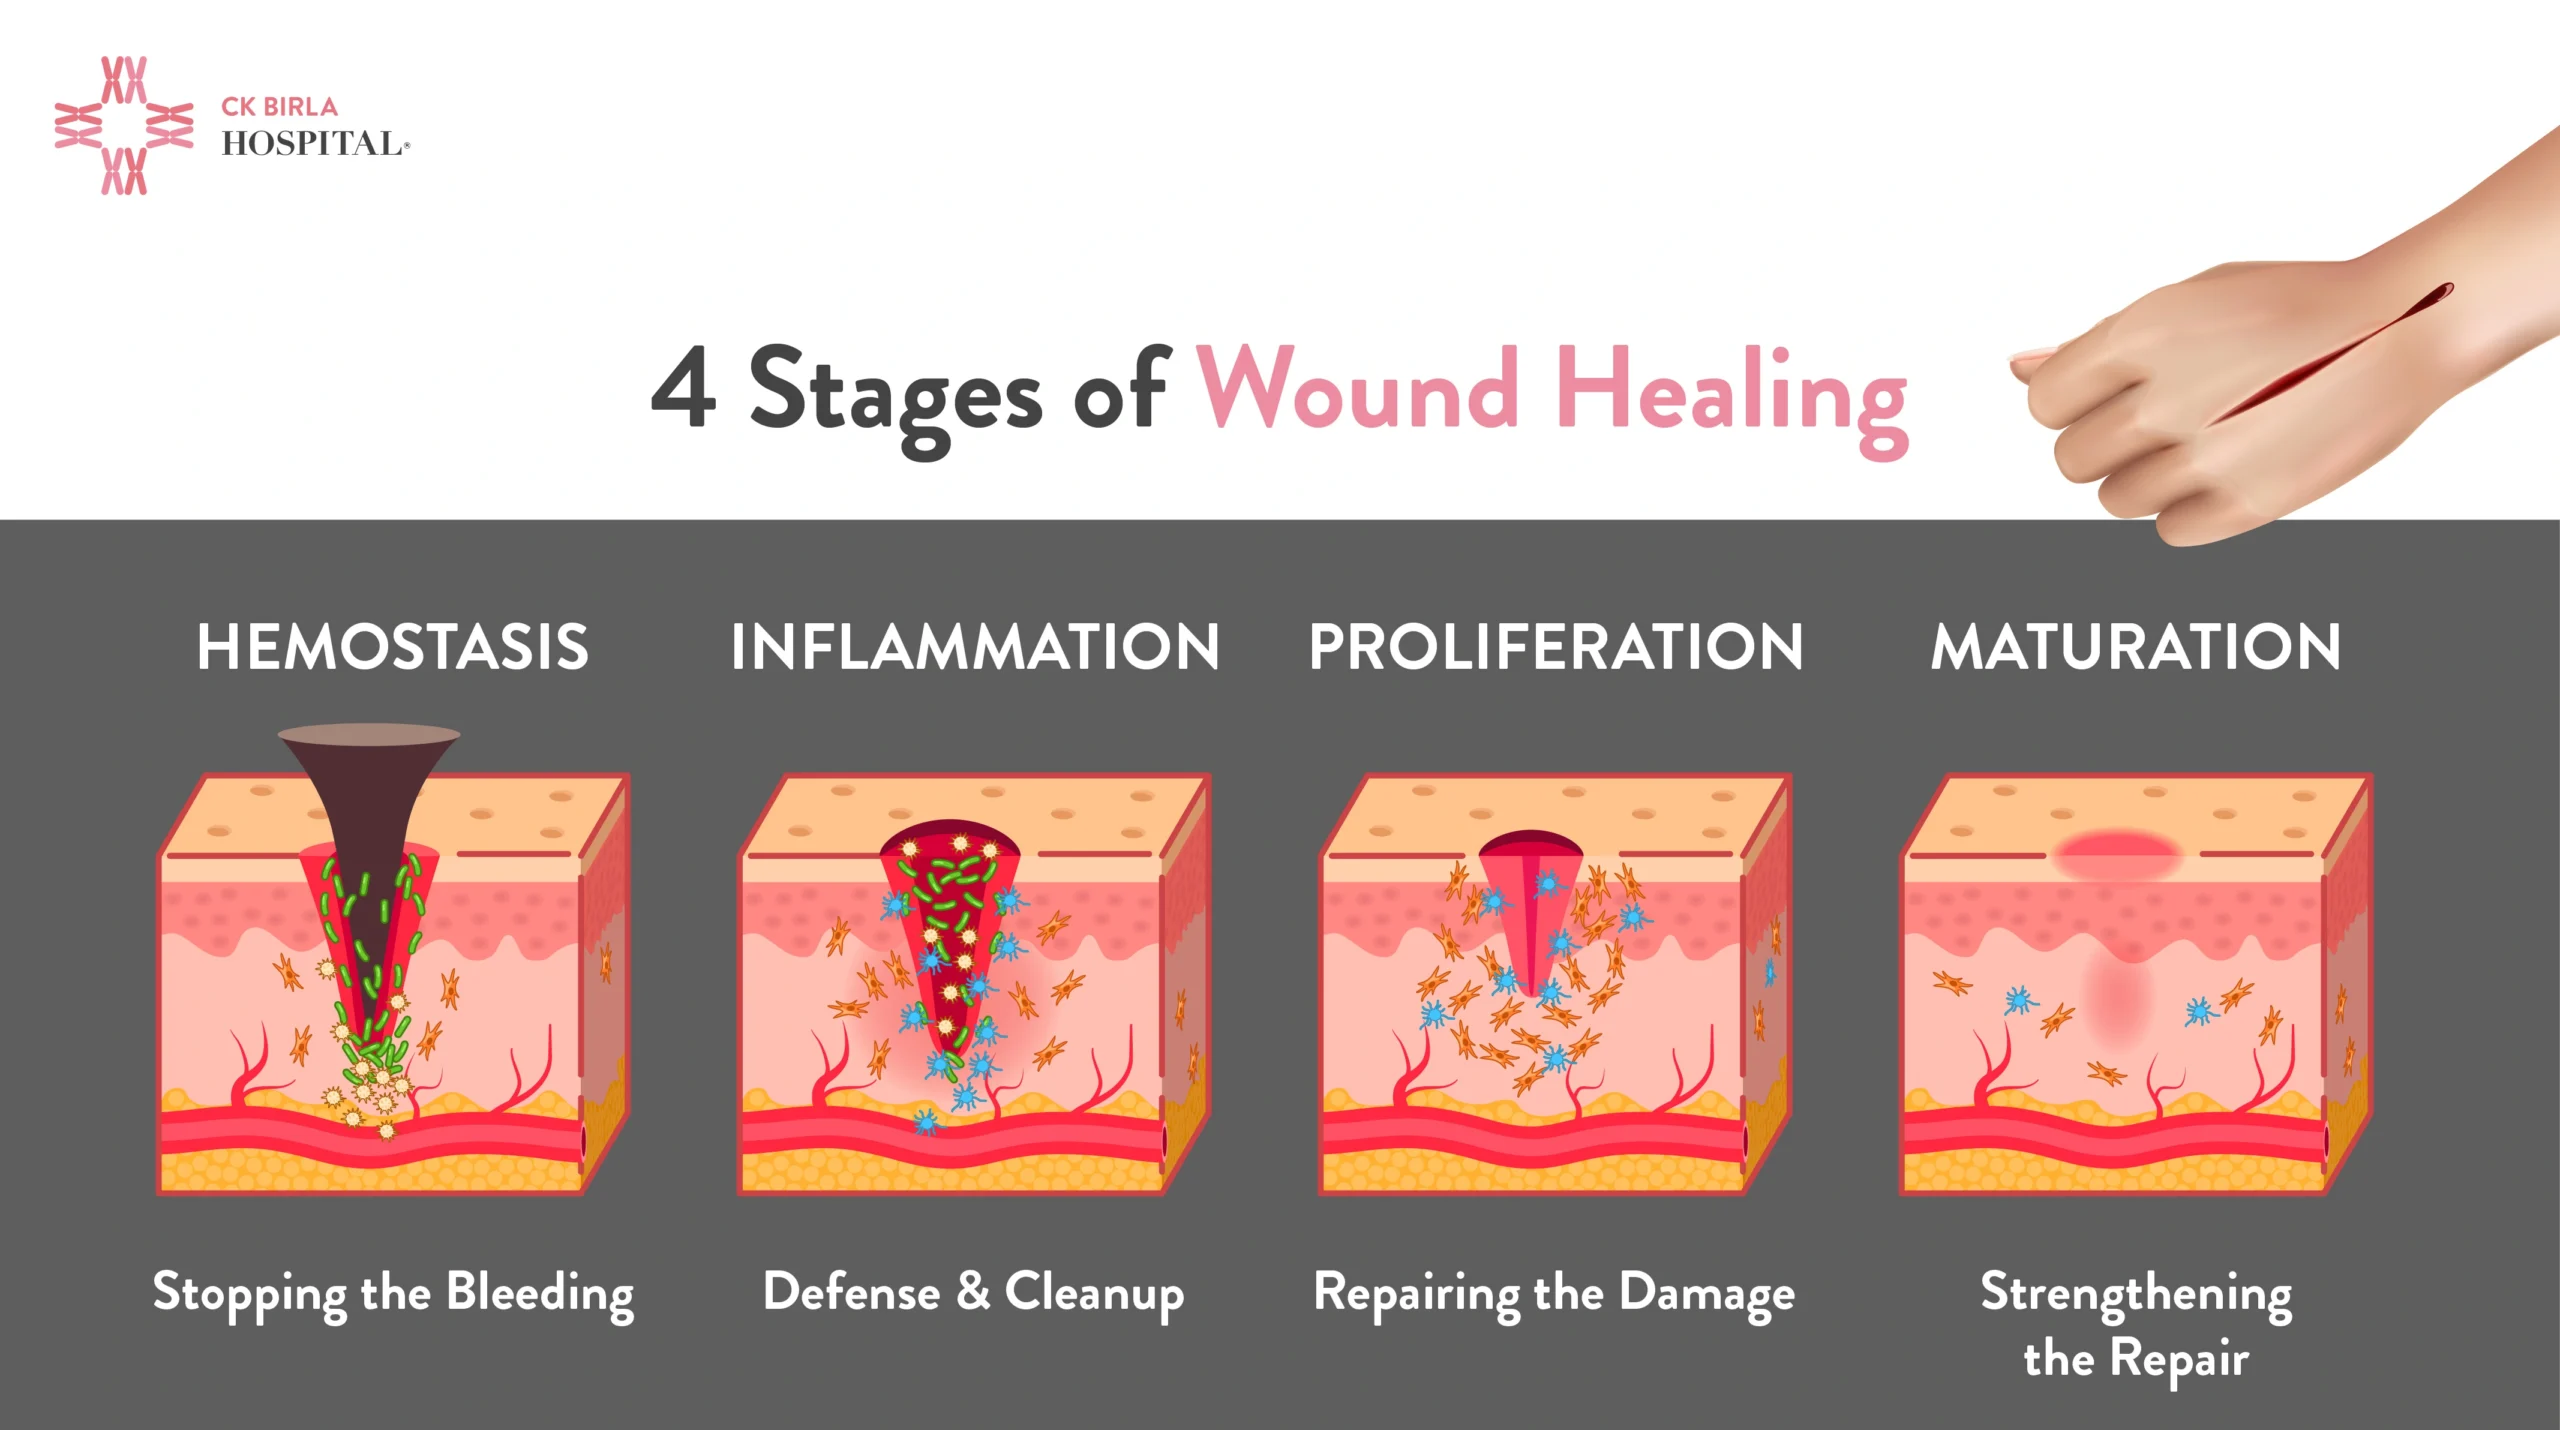
Trauma professionals rely on systematic diagnostic hierarchies to establish an accurate trauma diagnosis. Superficial appearances often conceal or exaggerate internal disruption. Skin elasticity, subcutaneous vascular density, and patient biomechanics produce misleading visual cues to an untrained observer.
[Patient Intake: ER / Field Triage]
│
▼
[Direct Examination & Vital Assessment]
│
┌────────────────┴────────────────┐
▼ ▼
[Penetrating Injury Protocol] [Blunt / Orthopedic Protocol]
• Margin inspection (soot/bevel) • Structural joint stability
• Cavitation depth evaluation • Radiographic / MRI imaging
• Medico-legal documentation • Grading: Grade I to III tears
In cases of suspected penetrating trauma, clinicians check for mechanical traits that distinguish ballistic projectiles from irregular metal, shattered glass, or blunt impact:
- Wound Margins: High-velocity rounds leave an abrasion collar along with localized tissue destruction. Irregular industrial punctures yield torn, asymmetric flaps without circumferential burn signatures.
- Tissue Cavitation: Modern medical imaging pinpoints shockwave pathways through muscle tissue. True projectile wounds feature internal cavitation far exceeding the outer diameter of the visible skin entry.
- Medico-Legal Chains of Custody: Forensic nurses secure physical specimens, clothing fibers, and chemical swabs under strict legal protocols to ensure reports remain defensible in judicial proceedings.
Evaluating athletic injuries follows similarly rigid protocols. Sports doctors classify muscle tears across three tiers: Grade I represents micro-tears across small muscle fascicles; Grade II involves a partial rupture with noticeable weakness; Grade III constitutes a full structural tear across the entire muscle belly or tendon junction. While a Grade I strain allows a fast return to competition, a full avulsion demands surgical re-anchoring and months of physical therapy. Establishing the correct tier depends on dynamic musculoskeletal ultrasound and MRI sequences, not touchline reactions.
James Sterling reports on renewable energy developments, climate policy, ecological conservation, and green tech innovations around the globe.
