Medical Breakdown: What Pituitary Gigantism Actually Does to the Human Body
 By Elena Rostova
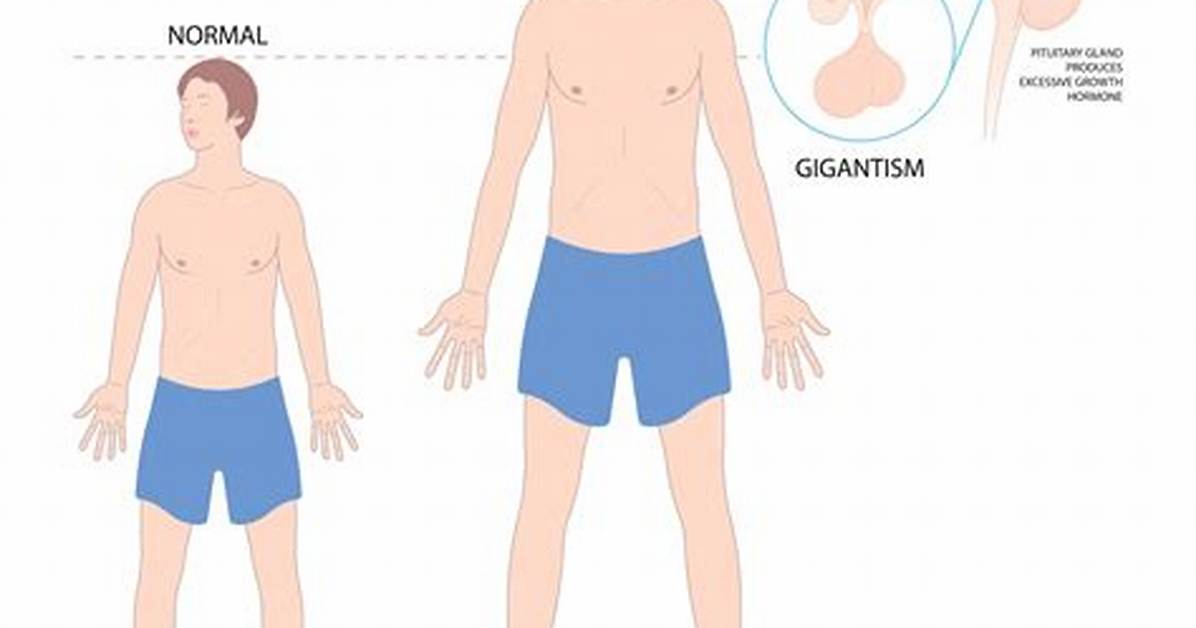
Recognizing that local facilities could not halt his rapid growth, Vovkovinskiy’s family relocated to Rochester, Minnesota, in 1989. The goal was to access specialized surgical and endocrinological care at the Mayo Clinic, one of the few centers equipped to handle pediatric skull-base neurosurgery at this scale.
Surgeons confronted a difficult clinical scenario. The pituitary adenoma was large and invasive, pressing dangerously close to the optic chiasm and internal carotid arteries. While surgical resection remains the front-line treatment for somatotroph tumors, complete removal becomes exceptionally difficult when the neoplastic tissue invades the surrounding cavernous sinus.
Vovkovinskiy underwent multiple transsphenoidal surgeries, radiation therapy, and complex pharmacotherapy designed to suppress hormone secretion. Somatostatin analogues, such as octreotide and lanreotide, alongside dopamine agonists, are routinely deployed to inhibit pituitary secretion, while growth hormone receptor antagonists like pegvisomant block peripheral IGF-1 production. Despite aggressive clinical management, residual tumor tissue and disrupted hormonal signaling continued to spur metabolic and skeletal changes throughout his adult life.
Elena Rostova holds a Master's degree in Public Health Journalism. She covers groundbreaking medical research, holistic wellness trends, mental health awareness, and nutritional science.
