New Clinical Warnings on Hand Weakness: When Slipping Grip Signals Serious Nerve Trouble
 By Chloe Bennett
For decades, public health messaging drilled carpal tunnel syndrome into the cultural lexicon. Whenever hand numbness causes concern, workers assume the median nerve is caught beneath the transverse carpal ligament at the base of the palm. Median nerve compression does account for widespread sensory loss across the thumb, index, and middle fingers, alongside atrophy of the thenar eminence. But it rarely explains the deep, disabling weakness that makes someone lose control of heavy objects.
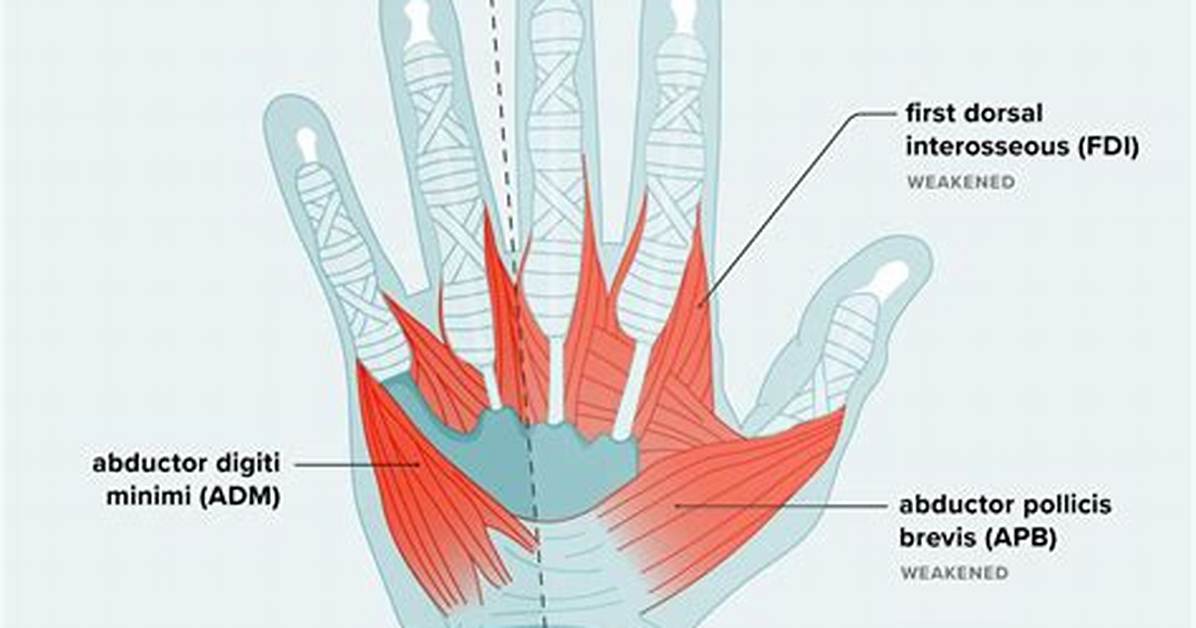
The true powerhouse of human grip strength is the ulnar nerve. Traversing a narrow bony groove behind the inner elbow, this nerve routes power to the intrinsic hand muscles, including the interossei and the adductor pollicis. When compressed at the elbow, a condition known as cubital tunnel syndrome, the consequence is catastrophic for manual force. Patients lose the ability to pinch firmly between the thumb and index finger, while the pinky and ring fingers curl weakly. Prolonged mobile device use, where the elbow remains bent past 90 degrees for hours at a time, stretches the ulnar nerve across the medial epicondyle like a taut cable, elevating internal pressure from a baseline of 7 mmHg to more than 24 mmHg.
Compounding this mechanical strain is ganglion cyst compression. While classic ganglion cysts present as visible, harmless bumps on the back of the wrist, "occult" cysts develop deep inside closed anatomical compartments. These hidden, fluid-filled sacs can sprout from the wrist joints, Guyon’s canal, or the elbow capsule. Because they remain invisible to the naked eye, they evade standard physical exams while exerting localized pressure against adjacent motor branches. The patient experiences accelerating weakness, entirely unaware that a pressurized cyst the size of an olive is suffocating vital nerve tissue.
Chloe Bennett explores the intersection of pop culture, streaming entertainment, digital trends, and contemporary lifestyle. Her weekly commentary reaches thousands of culture enthusiasts.
