Cna Point of Care at the Breaking Point: Inside the Battle over Staffing Ratios and Digital Bedside Demands
 By David Miller
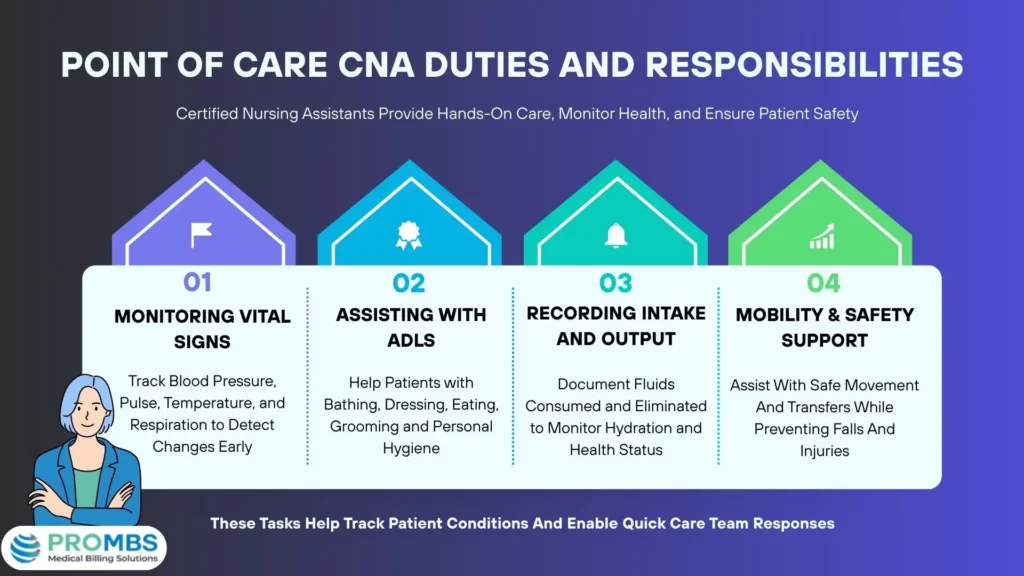
Activities of daily living tracking represents the core currency of long-term care reimbursement under Medicare’s Patient-Driven Payment Model (PDPM). When CNAs document that an 84-year-old resident with dementia required extensive two-person assistance for bed mobility and eating, the facility bills at a significantly higher reimbursement rate. If an aide is rushed and mistakenly charts "limited assistance," the nursing home forfeits thousands of dollars in monthly revenue.
This dynamic shifts managerial pressure downward onto the lowest-paid workers in the medical hierarchy. Supervisory registered nurses and Minimum Data Set (MDS) coordinators frequently audit electronic logs mid-shift, pulling aides away from call lights to correct omissions.
The psychological toll is immense. Frontline aides describe feeling monitored like distribution center warehouse workers rather than healthcare providers. When automated prompt boxes display messages asking why a resident’s repositioning was logged 20 minutes behind the scheduled two-hour turning window, the system ignores that the aide was in another room managing an active fall. The machine records only a non-compliant latency flag, skewing compliance metrics and generating administrative friction.
David Miller brings 15 years of experience in global economics, personal finance strategy, and market dynamics. He specializes in turning complex economic trends into actionable insights for everyday readers.
